

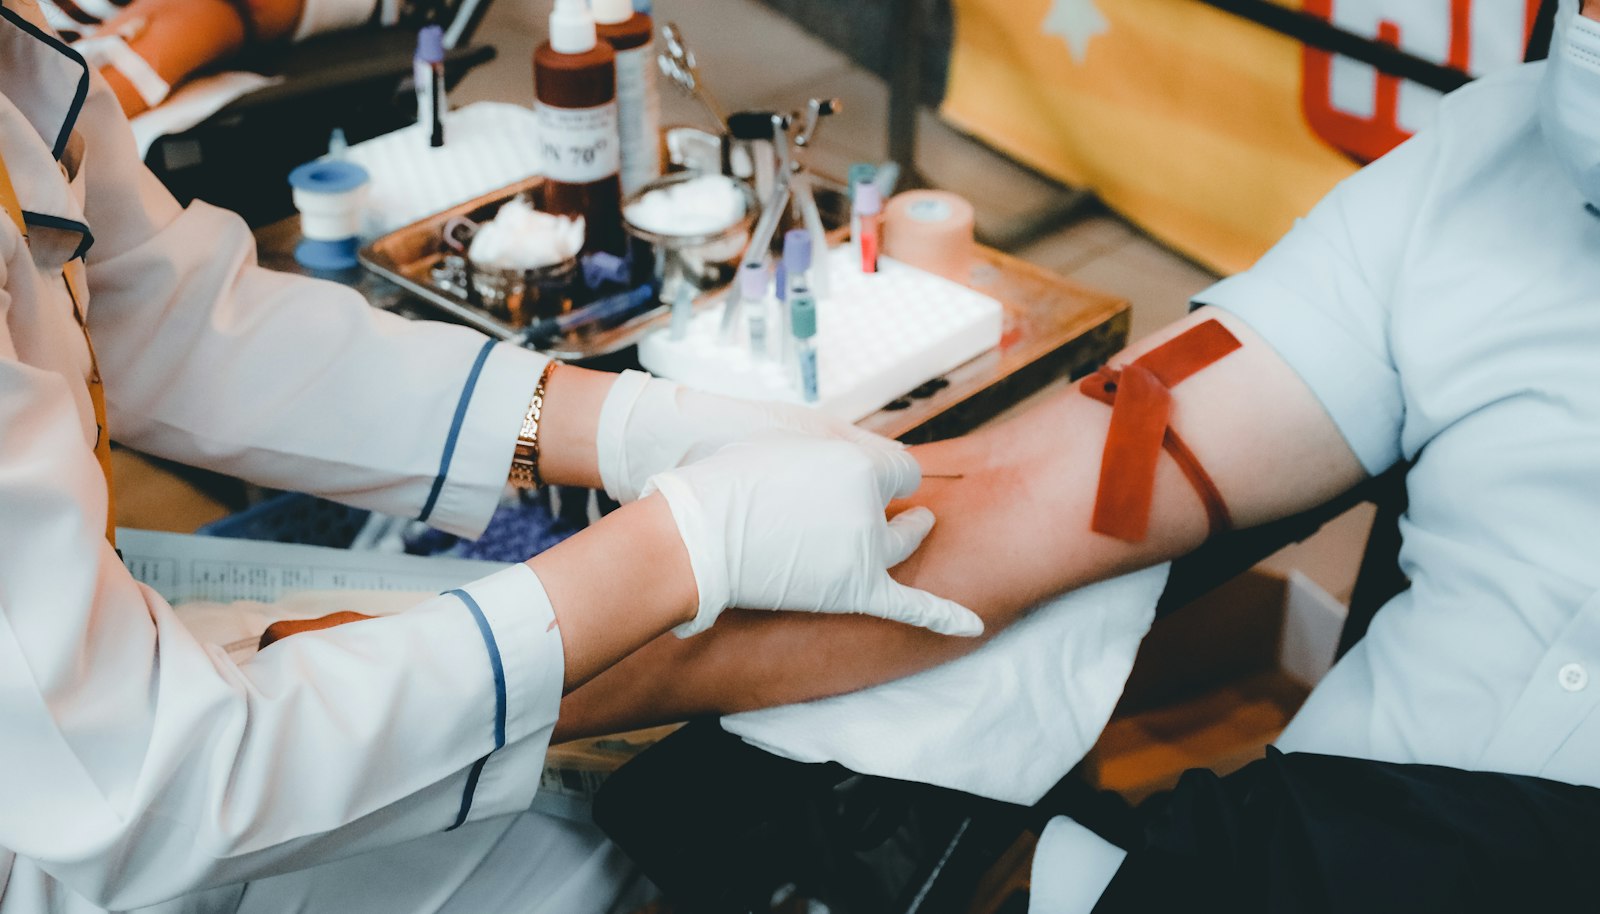
If you were diagnosed with low testosterone a few years ago, or you are just now considering getting tested, the landscape looks meaningfully different in 2026. Diagnostic standards have tightened, new biomarkers have entered routine clinical practice, and telehealth platforms have reshaped how men in Tempe, Arizona access testing and follow-up care. Knowing what has changed helps you ask smarter questions and get more accurate answers from your clinician.
Low testosterone, or hypogonadism, affects roughly 2 to 4 percent of men according to the Endocrine Society, but many researchers believe that number is underreported because older testing models relied too heavily on a single total testosterone reading. That single number is no longer considered sufficient by most leading endocrinology guidelines updated in 2025 and early 2026. A broader, more individualized approach is now the standard of care.
This guide breaks down what has genuinely changed in low T testing, why those changes matter, and what men in Tempe who are exploring testosterone replacement therapy should expect from a modern diagnostic workup. Whether you are brand new to this conversation or returning after years on TRT, the updates below are relevant to your care.
The Shift Away from Total Testosterone Alone
For decades, a total testosterone reading below 300 ng/dL was the rough threshold most physicians used to diagnose low T. That benchmark was always a simplification. The Endocrine Society and the American Urological Association have both updated their clinical practice guidelines to emphasize that total testosterone must be interpreted alongside free testosterone, sex hormone-binding globulin (SHBG), and symptom burden.
SHBG is a protein that binds testosterone, making it unavailable for use by your cells. A man can have a technically normal total testosterone reading but very high SHBG, leaving very little biologically active, or free, testosterone in circulation. Without measuring SHBG and calculating free testosterone, that man could be dismissed as normal when he is functionally deficient. Updated 2025 Endocrine Society guidelines explicitly call for SHBG measurement as part of any complete low T workup.
What a Modern Low T Panel Looks Like in 2026
A thorough diagnostic panel ordered by a qualified clinician in 2026 typically includes the following:
- Total testosterone – measured via early morning blood draw, ideally on two separate days
- Free testosterone – calculated or measured by equilibrium dialysis, the most accurate method
- Sex hormone-binding globulin (SHBG) – essential for accurate free T interpretation
- Luteinizing hormone (LH) and follicle-stimulating hormone (FSH) – to determine whether low T is primary or secondary in origin
- Estradiol (E2) – elevated estrogen in men can suppress testosterone and cause independent symptoms, as covered in our post on TRT and estrogen balance
- Complete blood count (CBC) – to evaluate red blood cell levels and hematocrit before and during TRT
- Comprehensive metabolic panel – including liver and kidney function markers
- Thyroid panel (TSH, free T3, free T4) – thyroid dysfunction mimics low T symptoms and is frequently overlooked
- Prolactin – elevated levels can indicate a pituitary issue causing secondary hypogonadism
- PSA (prostate-specific antigen) – baseline measurement required before any TRT is considered in men over 40
Two Morning Draws Are Now the Standard
One of the most significant procedural changes in 2026 guidelines is the firm recommendation for two separate morning testosterone measurements before any diagnosis is confirmed. Testosterone levels fluctuate naturally, and a single low reading can result from stress, poor sleep, illness, or simply testing at the wrong time of day.
According to Mayo Clinic reference ranges, testosterone peaks between 7 and 10 a.m. and can be 20 to 30 percent lower by afternoon. Men who were previously diagnosed based on a single late-morning draw may have received an inaccurate picture of their baseline. If your original diagnosis was based on one test, it may be worth revisiting with a clinician who follows updated protocols.
Digital and At-Home Testing: Useful but Limited
The telehealth boom has brought finger-prick testosterone kits and saliva-based hormone tests to the consumer market. These products are convenient and have improved in accuracy, but they are not equivalent to venipuncture laboratory testing analyzed by a certified clinical lab. The NIH cautions that saliva and capillary blood tests for testosterone have wider variability than standard serum assays.
Consumer kits can be a reasonable screening tool to decide whether a full clinical evaluation is worthwhile. However, a diagnosis of hypogonadism and any decision to begin TRT must be based on certified laboratory results, not an at-home kit. If you are in Tempe and a telehealth platform is managing your care, confirm that your blood draws go through a CLIA-certified laboratory.
Symptom Scoring Tools Are Now Part of the Workup
Labs alone do not tell the full story. In 2026, most clinicians following updated Endocrine Society guidance use validated symptom questionnaires such as the Androgen Deficiency in Aging Males (ADAM) questionnaire or the Aging Males Symptoms (AMS) scale as part of every initial evaluation. These tools capture fatigue, mood changes, reduced libido, cognitive fog, and other quality-of-life markers that numbers on a lab report cannot quantify.
Symptoms like persistent fatigue and mood disruption are often what drive men to seek care in the first place. Understanding how to present those symptoms clearly to your provider is important, which is why we recommend reading our guide on how to talk to your doctor about low T before your appointment.
Secondary Hypogonadism Gets More Attention in 2026
Primary hypogonadism means the testes themselves are not producing enough testosterone. Secondary hypogonadism means the signaling from the brain, specifically the hypothalamus and pituitary gland, is the problem. The distinction matters enormously for treatment decisions.
Updated guidelines now push clinicians to actively investigate secondary causes before defaulting to exogenous testosterone. Common secondary causes include obesity, obstructive sleep apnea, opioid use, hyperprolactinemia, and pituitary tumors. Treating the underlying cause may restore testosterone naturally, preserving fertility and avoiding lifelong TRT dependence. This is especially relevant for younger men in their 30s and early 40s who present with low T symptoms.
Monitoring Protocols Have Tightened
If you are already on TRT in Tempe, the monitoring recommendations you follow may also have been updated. Peer-reviewed research published in the Journal of Clinical Endocrinology and Metabolism in late 2024 reinforced quarterly testing during the first year of TRT, with particular attention to hematocrit, PSA, and cardiovascular markers.
Our detailed guide on TRT monitoring frequency covers what you should be tracking and when. Skipping labs is one of the most common mistakes men make once they feel better on therapy. In 2026, the clinical consensus is clear: consistent monitoring is non-negotiable for safe, effective TRT management.
What This Means for Men in Tempe, Arizona
Access to updated testing protocols varies significantly by provider. Not every general practitioner in Tempe will order a full modern panel on the first visit. Seeking care from a clinic that specializes in men’s hormonal health, or an endocrinologist who stays current with Endocrine Society guidelines, gives you the best chance of an accurate diagnosis and an appropriate treatment plan.
Ask your provider directly whether they follow the two-morning-draw protocol, whether they measure SHBG alongside total testosterone, and whether they use a validated symptom scoring tool. These are reasonable, informed questions that any qualified clinician should welcome.
Frequently Asked Questions
Why does my doctor need two blood draws to diagnose low T?
Testosterone levels fluctuate naturally from day to day and throughout the day. A single reading can be misleadingly low due to stress, illness, or poor sleep. Two separate morning measurements reduce the chance of a false positive diagnosis and are now recommended by the Endocrine Society before any treatment decision is made.
What is SHBG and why does it matter for low T testing?
Sex hormone-binding globulin (SHBG) is a protein that binds testosterone and prevents it from being used by your cells. High SHBG can leave you functionally testosterone-deficient even when your total testosterone number looks normal. Measuring SHBG allows your clinician to calculate free testosterone, which is a more accurate picture of your hormonal status.
Are at-home testosterone tests reliable in 2026?
Consumer finger-prick and saliva kits have improved but still carry wider variability than certified lab venipuncture testing. They are useful for initial screening but cannot legally or medically replace certified laboratory results when diagnosing hypogonadism or initiating TRT. Always confirm that your formal testing uses a CLIA-certified lab.
Can secondary hypogonadism be reversed without TRT?
Yes, in many cases. If low testosterone is caused by obesity, sleep apnea, opioid use, or a pituitary issue, treating the underlying cause may restore normal testosterone production. This is why updated 2026 guidelines emphasize investigating root causes, particularly in younger men, before beginning exogenous testosterone therapy.
What symptoms should I bring up when getting tested for low T?
Clinicians now use validated questionnaires to capture symptoms beyond low libido, including fatigue, mood changes, difficulty concentrating, reduced muscle mass, increased body fat, and poor sleep quality. Be specific and honest about all symptoms, even ones that seem unrelated to hormones, so your provider can score your symptom burden accurately.
How often should I get labs if I am already on TRT?
Most current guidelines recommend testing every 3 months during the first year of TRT, then shifting to every 6 to 12 months once your levels are stable. Key markers to monitor include total and free testosterone, hematocrit, PSA, and a metabolic panel. Your clinician may adjust this schedule based on your individual response to therapy.
Does the time of day I get my blood drawn really matter?
Yes, significantly. Testosterone peaks between 7 and 10 a.m. and can drop 20 to 30 percent by afternoon according to Mayo Clinic reference data. An afternoon draw can produce a falsely low result that does not reflect your true baseline. Always schedule your testosterone blood draw as early in the morning as possible, ideally before 9 a.m.
Disclaimer
This blog is for informational and educational purposes only and does not constitute medical advice. The content provided focuses on general education about testosterone, low testosterone, and testosterone replacement therapy (TRT). Individual health needs vary, and what applies to one person may not be appropriate for another.
Testosterone therapy is a prescription treatment that requires evaluation, lab testing, and ongoing monitoring by a licensed healthcare provider. Always consult a qualified physician before starting, stopping, or changing any medication, hormone therapy, or treatment plan.
If you are experiencing a medical emergency, call 911 or your local emergency services immediately. The information on this website does not create a doctor-patient relationship and should not be used as a substitute for professional medical advice, diagnosis, or treatment.

